
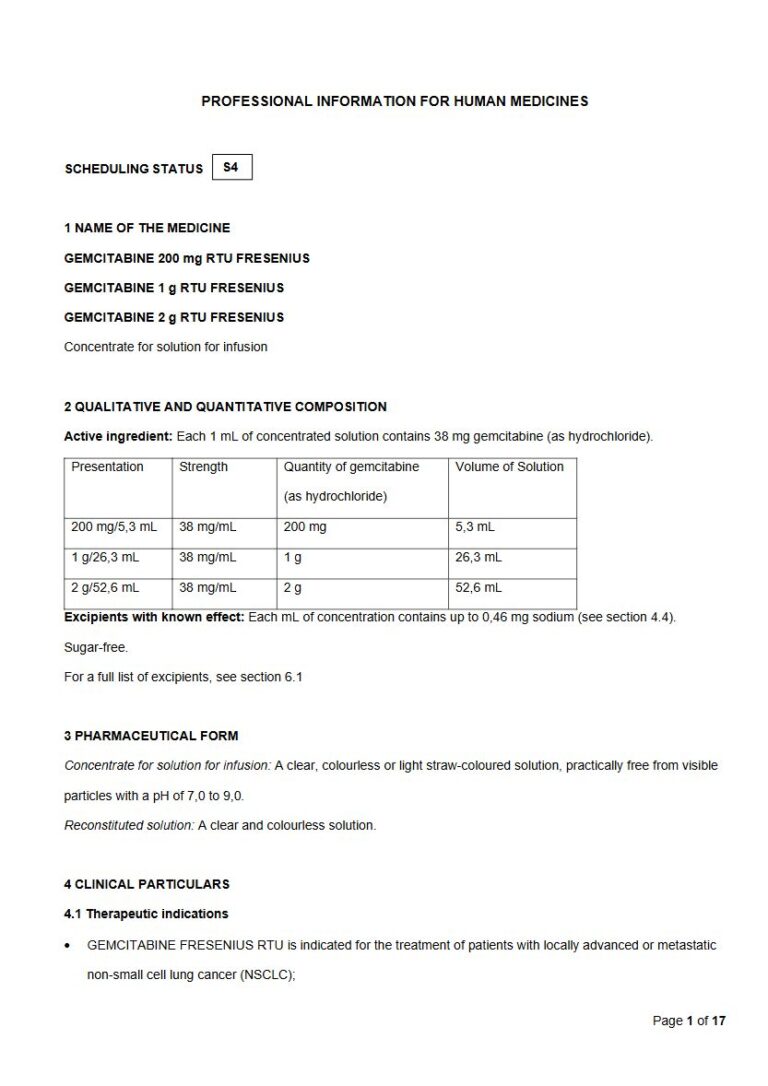
Gemcitabine 200 Mg/1 g/2 g Solution
PDF Leaflet Revision Date: 30 August 2024
Clinical Summary
Quick overview from the medicine insert
Indication
Treatment of various cancers including NSCLC, pancreatic, bladder, breast, and ovarian cancers.
Dosage (summary)
1,000 mg/mu00b2 IV infusion weekly for NSCLC and pancreatic cancer; 1,250 mg/mu00b2 for bladder cancer.
Special Populations
- Hepatic impairment
- Renal impairment
- Elderly patients
Pregnancy & Breastfeeding
Not established; avoid in pregnancy and breastfeeding.
Key Drug Interactions
- Cisplatin
- Paclitaxel
- Radiotherapy
Contraindications
- Hypersensitivity to gemcitabine
- Pregnancy
- Breastfeeding
- Children
Common side effects
- Nausea
- Vomiting
- Leucopenia
- Thrombocytopenia
- Allergic skin rash
Counselling Points
- Monitor for signs of toxicity
- Avoid pregnancy during treatment
- Inform about potential skin reactions
Serious warnings
- Haematological toxicity
- Capillary leak syndrome
- Pulmonary toxicity
- Posterior reversible encephalopathy syndrome
Important Disclaimer
The Gemcitabine 200 Mg/1 g/2 g Solution professional information leaflet below is the property of Fresenius Kabi South Africa and is provided on Medinsert exactly as issued, with no.. alterations or editorial changes. We make every effort to keep content current by updating documents as soon as new versions become available. Medinsert serves as a trusted access point for healthcare professionals, but does not replace official sources or clinical judgement. For more details, please read our full disclaimer. read more>>
 Healthcare Professionals Only
This content is for registered healthcare professionals
Sign in or create a free account to read the full package insert.
Free for HPCSA-registered professionals. Powered by Medinsert.
Clinical Particulars
Section 4 of the official insert — extracted exactly as issued, no alterations
4.1 Therapeutic indications
- GEMCITABINE FRESENIUS RTU is indicated for the treatment of patients with locally advanced or metastatic non-small cell lung cancer (NSCLC);
- GEMCITABINE FRESENIUS RTU is indicated as first-line treatment for patients with locally advanced (non-resectable Stage II or Stage III) or metastatic (Stage IV) adenocarcinoma of the pancreas;
- GEMCITABINE FRESENIUS RTU is indicated for patients previously treated with 5-Fluorouracil (5-FU);
- GEMCITABINE FRESENIUS RTU is indicated for treatment of patients with transitional cell bladder cancer;
- GEMCITABINE FRESENIUS RTU, in combination with paclitaxel, is indicated for the treatment of patients with unresectable, locally recurrent or metastatic breast cancer, in patients who have relapsed following adjuvant/neoadjuvant chemotherapy. Prior chemotherapy should have included an anthracycline, unless clinically contraindicated;
- GEMCITABINE FRESENIUS RTU, alone or in combination, is indicated for the treatment of patients with recurrent epithelial ovarian carcinoma who have relapsed following platinum-based chemotherapy.
4.2 Posology and method of administration
GEMCITABINE FRESENIUS RTU should only be prescribed by a medical doctor qualified in the use of anticancer chemotherapy.
Posology
Non-small cell lung cancer
Adults: The recommended monochemotherapy dose of GEMCITABINE FRESENIUS RTU is 1 000 mg/m2, given by 30-minute intravenous infusion. This should be repeated once a week for three consecutive weeks, followed by a 1-week rest period. This 4-week cycle is then repeated. Dosage reduction with each cycle or within a cycle may be applied, based upon the grade of toxicity experienced by the patient.
GEMCITABINE FRESENIUS RTU may be used in combination with cisplatin, using either a 3-week or a 4-week schedule. One of the following regimens is suggested:
3-week schedule: GEMCITABINE FRESENIUS RTU 1 250 mg/m2, given by 30-minute intravenous infusion on days 1 and 8 of every 21-day treatment cycle and cisplatin 100 mg/m2 on day 1. Dosage reduction with each cycle or within a cycle may be applied based upon the grade of toxicity experienced by the patient.
4-week schedule: GEMCITABINE FRESENIUS RTU 1 000 mg/m2 on days 1, 8, and 15 of every 28 days cycle and cisplatin 100 mg/m2 on either day 1, 2, or 15 of therapy. Dosage reduction with each cycle or within a cycle may be applied based upon the grade of toxicity experienced by the patient.
Pancreatic cancer
Adults: The recommended dose for GEMCITABINE FRESENIUS RTU is 1000 mg/m2, given by 30-minute intravenous infusion. This should be repeated once weekly for up to 7 weeks followed by a week of rest. Subsequently cycles should consist of injections once weekly for three consecutive weeks out of every 4 weeks. Dosage reduction with each cycle or within a cycle may be applied upon the grade of toxicity experienced by the patient.
Bladder cancer
Adults: The recommended monochemotherapy dosage of GEMCITABINE FRESENIUS RTU is 1 250 mg/m2, given by 30-minute intravenous infusion. The dose should be given on days 1, 8 and 15 of each 28-day cycle. This 4-week cycle is then repeated. Dosage reduction with each cycle or within a cycle may be applied based upon the grade of toxicity experienced by the patient.
GEMCITABINE FRESENIUS RTU may be used in combination with cisplatin. The recommended dosage of GEMCITABINE FRESENIUS RTU is 1 000 mg/m2, given by 30-minute intravenous infusion. The dose should be given at a recommended dose of 70 mg/m2 on day 1 following GEMCITABINE FRESENIUS RTU, or day 2 of each 28-day cycle. This 4-week cycle is then repeated. Dosage reduction with each cycle or within a cycle may be applied based upon the grade of toxicity experienced by the patient. More myelosuppression occurred when cisplatin was used in doses of 100 mg/m2.
Breast cancer
Adults: GEMCITABINE FRESENIUS RTU in combination with paclitaxel is recommended, using paclitaxel (175 mg/m2) administered on day 1 over approximately 3 hours as an intravenous infusion, followed by gemcitabine (1 250 mg/m2) as a 30-minute intravenous infusion on day 1 and 8 of each 21-day cycle. Dose reduction with each cycle or within a cycle may be applied based upon the grade of toxicity experienced by the patient. Patients should have an absolute granulocyte count of at least 1 500 (x 106/L) prior to initiation of GEMCITABINE FRESENIUS RTU + paclitaxel combination.
Ovarian cancer
Monotherapy: Adults: The recommended dose of GEMCITABINE FRESENIUS RTU is 800 - 1 250 mg/m2, given by a 30-minute intravenous infusion. The dose should be given on days 1, 8 and 15 of each 28-day cycle. This 4-week cycle is then repeated. Dosage reduction with each cycle or within a cycle may be applied based upon the amount of toxicity experienced by the patient.
Combination use: Adults: GEMCITABINE FRESENIUS RTU in combination with carboplatin is recommended, using GEMCITABINE FRESENIUS RTU 1 000 mg/m2 administered on days 1 and 8 of each 21-day cycle as a 30-minute intravenous infusion. After GEMCITABINE FRESENIUS RTU, carboplatin will be given on day 1 consistent with a target AUC of 4,0 mg/mL/min. Dose reduction with each cycle may be applied upon the grade of toxicity experienced by the patient.
Patients receiving GEMCITABINE FRESENIUS RTU should be monitored prior to each dose for platelet, leucocyte and granulocyte counts and, if necessary, the dose of GEMCITABINE FRESENIUS RTU may be reduced or withheld in the presence of haematological toxicity, according to the following scale:
Absolute granulocyte count (x 106/L) Platelet count (x 106/L) Percentage of full dose
> 1 000 and > 100 000 100
500-1 000 or 50 000-100 000 75
< 500 or < 50 000 withhold
Periodic physical examination and checks of renal and hepatic function should be made to detect non-haematologic toxicity. Dosage reduction with each cycle may be applied based upon the amount of toxicity experienced by the patient. Doses should be withheld until toxicity has resolved in the opinion of the doctor.
GEMCITABINE FRESENIUS RTU can be administrated on an outpatient basis.
Special populations
Patients with hepatic or renal impairment: GEMCITABINE FRESENIUS RTU should be used with caution in patients with hepatic insufficiency or with impaired renal function as no studies have been done in patients with significant renal or hepatic impairment. There is insufficient data to allow clear dose recommendation for this patient population.
Elderly patients: GEMCITABINE FRESENIUS RTU has been widely used in patients over the age of 65. There is no evidence to suggest that dose adjustments are necessary in the elderly, although gemcitabine clearance and half-life are affected by age.
Paediatric population: The safety and efficacy of GEMCITABINE FRESENIUS RTU in children have not been established (see section 4.3).
Method of administration
For IV administration only. GEMCITABINE FRESENIUS RTU is administered as a 30-minute intravenous infusion. The only approved diluent for GEMCITABINE FRESENIUS RTU is 0,9 % sodium chloride. It is not recommended that GEMCITABINE FRESENIUS RTU be mixed with other medicines when diluted. For instructions for reconstitution, see section 6.6.
4.3 Contraindications
- Hypersensitivity to gemcitabine or to any of the excipients of GEMCITABINE FRESENIUS RTU.
- Pregnancy and breastfeeding: the safety of GEMCITABINE FRESENIUS RTU in human pregnancy and lactation has not been established (see section 4.6).
- Usage in children: safety and efficacy in children have not been established.
4.4 Special warnings and precautions for use
Patients receiving therapy with GEMCITABINE FRESENIUS RTU should be monitored closely by experienced staff in specialised centres. Treatment for a patient compromised by medicine toxicity may be required. Prolongation of the infusion time and increased dosing frequency have been shown to increase toxicity. Laboratory facilities should be available to monitor patient status.
Haematological toxicity
GEMCITABINE FRESENIUS RTU may suppress bone marrow function as manifested by leucopoenia, thrombocytopenia and anaemia. Patients receiving GEMCITABINE FRESENIUS RTU should be monitored prior to each dose for platelet, leucocyte and granulocyte counts. The possibility of cumulative bone marrow suppression when using combination or sequential chemotherapy should be considered. Suspension or modification of therapy should be considered when medicine-induced bone marrow depression is detected (see section 4.2).
Peripheral blood counts may continue to deteriorate after GEMCITABINE FRESENIUS RTU administration has been stopped. In patients with impaired bone marrow function, the treatment should be started with caution. The risk of cumulative bone marrow suppression should be considered when GEMCITABINE FRESENIUS RTU treatment is given together with other chemotherapy.
Hepatic and renal impairment
GEMCITABINE FRESENIUS RTU should be used with caution in patients with hepatic or renal function impairment as there is insufficient information to allow clear dose recommendation for this patient population (see section 4.2). Administration of GEMCITABINE FRESENIUS RTU in patients with concurrent liver metastases or a pre-existing medical history of hepatitis, alcoholism or liver cirrhosis may lead to exacerbation of the underlying hepatic impairment. Laboratory evaluation of renal and hepatic function (including virologic tests) should be performed periodically.
Live vaccinations
Yellow fever vaccine and other live attenuated vaccines are not recommended in patients treated with GEMCITABINE FRESENIUS RTU (see section 4.5).
Nervous system
Posterior reversible encephalopathy syndrome
Reports of posterior reversible encephalopathy syndrome (PRES) with potentially severe consequences have been reported in patients receiving gemcitabine (as in GEMCITABINE FRESENIUS RTU) as single therapy or in combination with other chemotherapeutic medicines. Acute hypertension and seizure activity were reported in most gemcitabine patients experiencing PRES, but other symptoms such as headache, lethargy, confusion and blindness could also be present. Diagnosis is optimally confirmed by magnetic resonance imaging (MRI). PRES is typically reversible with appropriate supportive measures. GEMCITABINE FRESENIUS RTU should be permanently discontinued, and supportive measures implemented, including blood pressure control and anti-seizure therapy, if PRES develops during therapy.
Cardiovascular
Due to the risk of cardiac and/or vascular disorders with GEMCITABINE FRESENIUS RTU, particular caution should be exercised with patients with a history of cardiovascular events.
Capillary leak syndrome
Capillary leak syndrome has been reported in patients receiving gemcitabine (as in GEMCITABINE FRESENIUS RTU) as single therapy, or in combination with other chemotherapeutic medicines (see section 4.8). The condition is usually treatable if recognised early and managed appropriately, but fatal cases have been reported. The condition involves systemic capillary hyperpermeability during which fluid and proteins from the intravascular space leak into the interstitium. The clinical features include generalised oedema, weight gain, hypoalbuminemia, severe hypotension, acute renal impairment and pulmonary oedema. GEMCITABINE FRESENIUS RTU should be discontinued, and supportive measures implemented if capillary leak syndrome develops during therapy. Capillary leak syndrome may occur in later cycles and has been associated in the literature with adult respiratory distress syndrome.
Pulmonary toxicity
Pulmonary effects, sometimes severe (such as pulmonary oedema, interstitial pneumonitis or adult respiratory distress syndrome (ARDS)) have been reported in association with gemcitabine (as in GEMCITABINE FRESENIUS RTU) therapy. If such effects develop, consideration should be made to discontinuing GEMCITABINE FRESENIUS RTU therapy. Early use of supportive care measure may help ameliorate the condition.
Renal toxicity
Renal failure and the haemolytic uremic syndrome (HUS) have been reported less frequently with gemcitabine use. GEMCITABINE FRESENIUS RTU should be administered with caution to patients with impaired renal function.
Haemolytic uremic syndrome (HUS)
Clinical findings consistent with HUS were reported in patients receiving gemcitabine (as in GEMCITABINE FRESENIUS RTU; see section 4.8). HUS is a potentially life-threatening disorder. GEMCITABINE FRESENIUS RTU should be discontinued at the first signs of any evidence of microangiopathic haemolytic anaemia, such as rapidly falling haemoglobin with concomitant thrombocytopenia, elevation of serum bilirubin, serum creatinine, blood urea, or LDH. Renal failure may not be reversible with discontinuation of therapy and dialysis may be required.
Carcinogenesis, mutagenesis, impairment of fertility
The carcinogenic potential of gemcitabine has not been established. Cytogenic damage has been produced by gemcitabine in an in vivo assay. It induced forward mutation in vitro in a mouse lymphoma assay.
Severe cutaneous adverse reactions (SCARs)
Severe cutaneous adverse reactions (SCARs) including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and acute generalized exanthematous pustulosis (AGEP), which can be life-threatening or fatal, have been reported in association with gemcitabine treatment. Patients should be advised of the signs and symptoms and monitored closely for skin reactions. If signs and symptoms suggestive of these reactions appear, gemcitabine should be withdrawn immediately.
4.5 Interactions with other medicines
No specific interaction studies have been performed.
Radiotherapy
Concurrent radiotherapy (given together, or u2264 7 days apart) - toxicity associated with this multimodality therapy is dependent on many different factors, including dose of GEMCITABINE FRESENIUS RTU, frequency of GEMCITABINE FRESENIUS RTU administration, dose of radiation, radiotherapy planning technique, the target tissue, and target volume. Studies indicated that gemcitabine (as in GEMCITABINE FRESENIUS RTU) has radiosensitising activity when GEMCITABINE FRESENIUS RTU at a dose of 1 000 mg/m2 is administered concurrently for up to six consecutive weeks with therapeutic thoracic radiation to patients with non-small cell lung cancer. Significant toxicity in the form of severe and potentially life-threatening mucositis, especially esophagitis, and pneumonitis is observed, particularly in patients receiving large volumes of radiotherapy (median treatment volumes 4 795 cm3). The optimum regimen for safe administration of gemcitabine (as in GEMCITABINE FRESENIUS RTU) with therapeutic doses of radiation has not been determined in all tumour types. Radiation injury has been reported on targeted tissues (e.g. esophagitis, colitis, and pneumonitis) in association with both concurrent and non-concurrent use of GEMCITABINE FRESENIUS RTU.
Live vaccines
Yellow fever and other live attenuated vaccines are not recommended due to the risk of systemic, possibly fatal, disease, particularly in immunosuppressed patients.
4.6 Fertility, pregnancy and lactation
Women of childbearing potential
Women should be advised not to become pregnant during treatment with GEMCITABINE FRESENIUS RTU and to inform their attending doctor immediately, should this occur. The duration of contraception for women following the end of treatment with GEMCITABINE FRESENIUS RTU is 6 months.
Pregnancy
The safety of GEMCITABINE FRESENIUS RTU in human pregnancy has not been established (see section 4.3). Studies in animals have shown reproductive toxicity.
Breastfeeding
It is not known whether gemcitabine is excreted in human milk (see section 4.3), and adverse effects on the suckling child cannot be excluded. Breastfeeding should be discontinued during therapy with GEMCITABINE FRESENIUS RTU (see section 4.3).
Fertility
Fertility studies showed that gemcitabine causes hypospermatogenesis in male mice. Therefore, men being treated with GEMCITABINE FRESENIUS RTU are advised not to father a child during and up to 6 months after treatment. Men should seek further advice regarding cryoconservation of sperm prior to treatment because of the possibility of infertility due to therapy with GEMCITABINE FRESENIUS RTU.
4.7 Effects on ability to drive and use machines
GEMCITABINE FRESENIUS RTU may cause mild to moderate somnolence. Patients should be cautioned against driving or operating machinery until it is established that they do not become drowsy.
4.8 Undesirable effects
a. Summary of the safety profile
The most commonly reported adverse reactions associated with gemcitabine (contained in GEMCITABINE FRESENIUS RTU) treatment include nausea with or without vomiting, raised liver transaminases (AST/ALT) and alkaline phosphatase, reported in approximately 60 % of patients; proteinuria and haematuria reported in approximately 50 % of patients; dyspnoea reported in 10-40 % of patients (highest incidence in lung cancer patients) and allergic skin rashes occurring in approximately 25 % of patients and associated with itching in 10 % of patients. The frequency and severity of the adverse reactions are affected by the dose, infusion rate and intervals between doses (see section 4.4). Dose-limiting adverse reactions are reductions in platelet, leucocyte and granulocyte counts (see section 4.2).
b. Tabulated list of adverse reactions
System organ class Frequency grouping Adverse events
Infections and infestations Frequent Infections Frequency unknown Sepsis
Blood and the lymphatic system disorders Frequent Leucopoenia, neutropenia, thrombocytopenia, anaemia, febrile neutropenia (see section 4.2 and 4.4) Less frequent Thrombocytosis, thrombotic microangiopathy
Immune system disorders Less frequent Anaphylactoid reaction
Metabolism and nutrition disorders Frequent Anorexia
Psychiatric disorders Frequent Insomnia Less frequent Somnolence
Nervous system disorders Frequent Headache Less frequent Posterior reversible encephalopathy syndrome (see section 4.4) Frequency unknown: Cerebrovascular accident
Cardiac disorders Less frequent Dysrhythmias - predominantly supraventricular in nature, heart failure, myocardial infarction
Vascular disorders Less frequent Clinical signs of peripheral vasculitis and gangrene, hypotension, capillary leak syndrome (see section 4.4)
Respiratory, thoracic and mediastinal disorders Frequent Dyspnoea u2013 usually mild and passes without treatment, cough, rhinitis Less frequent Interstitial pneumonitis (see section 4.4), bronchospasm u2013 usually mild and transient but may require parenteral treatment, pulmonary oedema, adult respiratory distress syndrome (see section 4.4) Frequency unknown Pulmonary eosinophilia
Gastrointestinal disorders Frequent Vomiting, nausea, diarrhoea, stomatitis and ulceration of the mouth, constipation Frequency unknown Ischaemic colitis
Hepatobiliary disorders Frequent Elevation of liver transaminases (AST and ALT) and alkaline phosphatase, increased bilirubin Less frequent Serious hepatotoxicity (including liver failure and death), increased gamma-glutamyl transferase (GGT).
Skin and subcutaneous tissue disorders Frequent Allergic skin rash frequently associated with pruritus, alopecia, itching, sweating Less frequent Severe skin reactions, including desquamation and bullous skin eruptions, ulceration, vesicle and sore formation, scaling, toxic epidermal necrolysis, Stevens-Johnson syndrome, pseudocellulitis Frequency unknown Acute generalised exanthematous pustulosis
Musculoskeletal and connective tissue disorders Frequent Back pain, myalgia
Renal and urinary disorders Frequent Haematuria, proteinuria Less frequent Renal failure (see section 4.4), haemolytic uremic syndrome (see section 4.4)
General disorders and administration site conditions Frequent Influenza-like symptoms (1), oedema, peripheral oedema, including facial oedema, fever, asthenia, chills Less frequent Injection site reactions
Injury, poisoning, and procedural complications Less frequent Radiation toxicity (see section 4.5), radiation recall
(1) Influenza-like symptoms may include fever, headache, chills, myalgia, asthenia and anorexia. Cough, rhinitis, malaise, perspiration and sleeping difficulties have also been reported.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicine is important. It allows continued monitoring of the benefit/risk balance of the medicine. Healthcare providers are requested to report any suspected adverse drug reactions to SAHPRA via the Med Safety APP (Medsafety X SAHPRA) and eReporting platform (who-umc.org) found on SAHPRA website. Healthcare providers are asked to report any suspected adverse drug reactions to the Holder of the Certificate of Registration at the following email address: [email protected] and to the relevant medicineu2019s regulatory authority in the country where the product is marketed.
4.9 Overdose
Symptoms
In overdose, side effects can be precipitated and/or be of increased severity (see section 4.8).
Management
There is no antidote for overdosage of GEMCITABINE FRESENIUS RTU. In the event of a suspected overdose, the patient should be monitored with appropriate blood counts and receive supportive therapy, as necessary.
