
Paclitaxel Viatris 30 mg/100 mg/300 mg Infusion
PDF Leaflet Revision Date: 27 April 2024
Clinical Summary
Quick overview from the medicine insert
Indication
Palliative treatment of advanced cancers including ovarian, breast, and non-small cell lung cancer.
Dosage (summary)
175 mg/mu00b2 IV over 3 hours every 3 weeks; adjust for neutrophil counts.
Special Populations
- Hepatic impairment
- Elderly
Pregnancy & Breastfeeding
Contraindicated in pregnancy; unknown if excreted in breast milk.
Key Drug Interactions
- Cisplatin
- Ketoconazole
- Doxorubicin
Contraindications
- Severe hypersensitivity to paclitaxel
- Neutrophils < 1500/mmu00b3
Common side effects
- Neutropenia
- Peripheral neuropathy
- Hypersensitivity reactions
- Nausea
- Vomiting
Counselling Points
- Premedicate with corticosteroids and antihistamines
- Monitor for hypersensitivity
- Avoid pregnancy during treatment
Serious warnings
- Severe hypersensitivity reactions
- Bone marrow suppression
- Cardiovascular events
Important Disclaimer
The Paclitaxel Viatris 30 mg/100 mg/300 mg Infusion professional information leaflet below is the property of Viatris South Africa and is provided on Medinsert exactly as issued, with no.. alterations or editorial changes. We make every effort to keep content current by updating documents as soon as new versions become available. Medinsert serves as a trusted access point for healthcare professionals, but does not replace official sources or clinical judgement. For more details, please read our full disclaimer. read more>>
 Healthcare Professionals Only
This content is for registered healthcare professionals
Sign in or create a free account to read the full package insert.
Free for HPCSA-registered professionals. Powered by Medinsert.
Clinical Particulars
Section 4 of the official insert — extracted exactly as issued, no alterations
4.1 Therapeutic indications
PACLITAXEL VIATRIS is indicated for:
- The palliative treatment of Stage 3 or 4 advanced local carcinoma of the ovary after surgical resection, in combination with cisplatin.
- The palliative management of metastatic carcinoma of the ovary after failure of first line or subsequent chemotherapy.
- The treatment of metastatic carcinoma of the breast after failure of combination chemotherapy or relapse within 6 months of adjuvant chemotherapy. Prior therapy should have included an anthracycline unless clinically contraindicated.
- Palliative treatment of advanced non-small cell lung cancer in patients who are not candidates for potentially curative surgery and/or radiation therapy.
4.2 Posology and method of administration
Indication 1: Primary treatment of ovarian carcinoma:
A combination regimen consisting of PACLITAXEL VIATRIS 175 mg/m2 administered intravenously over 3 hours, followed by cisplatin 75 mg/m2 given every 3 weeks. Alternatively a combination regimen consisting of PACLITAXEL VIATRIS 135 mg/mu00b2 administered over 24 hours, followed by cisplatin 75 mg/mu00b2, every 3 weeks. PACLITAXEL VIATRIS should be administered before cisplatin.
Indications 2 and 3: Secondary treatment of ovarian and breast cancer:
PACLITAXEL VIATRIS at a dose of 175 mg/mu00b2 administered intravenously over 3 hours every 3 weeks has been shown to be effective in patients with metastatic carcinoma of the ovary or breast after the failure of first line or subsequent chemotherapy.
Indication 4: Palliative treatment of advanced non-small cell lung carcinoma:
the recommended dose of PACLITAXEL VIATRIS is 175 mg/mu00b2 administered over a period of 3 hours; followed by a platinum compound, with a 3 week interval between courses. PACLITAXEL VIATRIS should not be re-administered until the neutrophil count is at least 1 500/mmu00b3 and the platelet count is at least 100 000/mmu00b3. Patients who experience severe neutropenia (neutrophil count < 500/mmu00b3) or moderate to severe peripheral neuropathy should receive a dose reduction of 20 % for subsequent courses (see section 4.4). The incidence and severity of neurotoxicity and haematologic toxicity increases with dose.
All patients must be premedicated with corticosteroids, antihistamines, and H 2 antagonists prior to PACLITAXEL VIATRIS administration, e.g. dexamethasone 20 mg orally approximately 12 and 6 hours before PACLITAXEL VIATRIS or 20 mg IV approximately 30 to 60 minutes prior to PACLITAXEL VIATRIS, promethazine 25 mg IV 30 to 60 minutes prior to PACLITAXEL VIATRIS and cimetidine 300 mg or ranitidine 50 mg IV 30 to 60 minutes before PACLITAXEL VIATRIS.
PACLITAXEL VIATRIS should be administered through an in-line filter with a microporous membrane not greater than 0,22 microns.
Special populations
Hepatic impairment: See section 4.4. Dosage adjustment is recommended as shown below:
| Transaminase levels | Bilirubin levels (a) | Recommended PACLITAXEL VIATRIS dose (b) |
|---|---|---|
| < 2 x ULN and u2264 1,5 mg/dl | < 10 x ULN | 135 mg/mu00b2 |
| 2-< 10 x ULN | 1,6 - 7,5 mg/dl | 100 mg/mu00b2 |
| u2265 10 x ULN or > 7,5 mg/dl | Not recommended |
Paediatric population: The safety and efficacy of PACLITAXEL VIATRIS in children has not been established (see section 4.4).
Method of administration
For intravenous use. For instructions on preparation, dilution, disposal and other handling, see section 6.6.
4.3 Contraindications
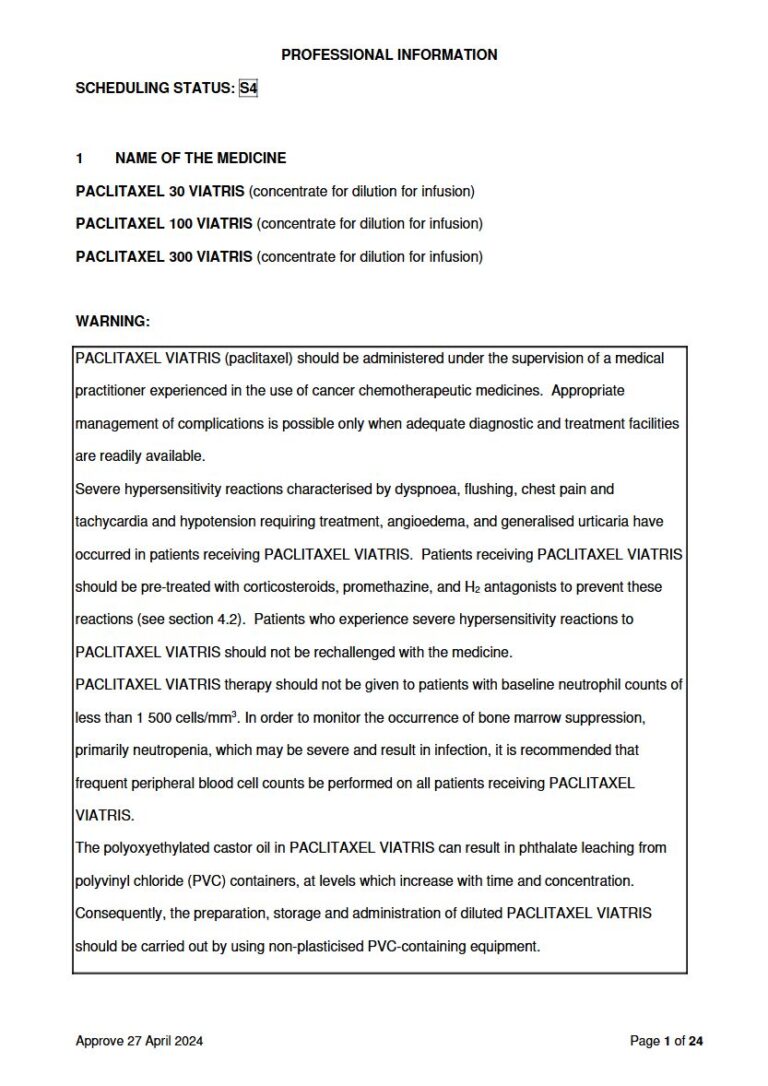
PACLITAXEL VIATRIS is contraindicated in patients who have a history of severe hypersensitivity reactions to paclitaxel or other medicines formulated with polyoxyethylated castor oil or to any of the excipients listed in section 6.1. PACLITAXEL VIATRIS should not be used in patients with baseline neutrophils < 1 500/mmu00b3. Pregnancy and lactation (see section 4.6). The safety and effectiveness of PACLITAXEL VIATRIS in children have not been established.
4.4 Special warnings and precautions for use
PACLITAXEL VIATRIS should be administered under the supervision of a medical practitioner experienced in the use of cancer chemotherapeutic medicines. Since severe hypersensitivity reactions may occur, appropriate supportive equipment should be available. PACLITAXEL VIATRIS should be administered as a diluted infusion. PACLITAXEL VIATRIS should be given before cisplatin when used in combination. Patients should be pre-treated with corticosteroids, antihistamines and H 2 antagonists before receiving PACLITAXEL VIATRIS.
Hypersensitivity reactions:
Anaphylaxis and severe hypersensitivity reactions, probably histamine-mediated, characterised by dyspnoea, flushing, chest pain and tachycardia and hypotension requiring treatment, angioedema and generalised urticaria have occurred in patients receiving PACLITAXEL VIATRIS. Patients with a history of severe hypersensitivity reactions to products containing Cremophor EL (e.g. ciclosporine for injection concentrate and teniposide for injection concentrate) should not be treated with PACLITAXEL VIATRIS. In order to avoid the occurrence of severe hypersensitivity reactions, all patients treated with PACLITAXEL VIATRIS should be premedicated with corticosteroids (such as dexamethasone), promethazine and H 2 antagonists (such as cimetidine or ranitidine). Rare fatal reactions have occurred in patients despite pre-treatment. In cases of severe hypersensitivity reactions, PACLITAXEL VIATRIS infusion should be immediately discontinued, symptomatic therapy should be initiated and the patient should not be rechallenged with the medicine. Minor hypersensitivity reactions such as flushing or rash do not require interruption of therapy.
Bone marrow suppression:
Bone marrow suppression (primary neutropenia) is the principal dose-limiting toxicity. Frequent monitoring of blood counts should be instituted during PACLITAXEL VIATRIS treatment. Patients should not be retreated with subsequent cycles of PACLITAXEL VIATRIS until neutrophils recover to a level >1 500 cells/mmu00b3 and platelets recover to a level > 100 000 cells/mmu00b3. In the case of severe neutropenia (< 500 cells/mmu00b3 for seven days or more) during a course of PACLITAXEL VIATRIS therapy, a 20 % reduction in dose for subsequent courses of therapy is recommended. The incidence of neurotoxicity and the severity of neutropenia increase with dose within a regimen.
Cardiovascular:
Severe cardiac conduction abnormalities have been reported. If patients develop significant conduction abnormalities during PACLITAXEL VIATRIS administration, appropriate therapy should be administered and continuous cardiac monitoring should be performed during subsequent therapy with PACLITAXEL VIATRIS. Severe cardiovascular events were observed more frequently in patients with non-small cell lung carcinoma than breast or ovarian carcinoma. Hypotension, hypertension and bradycardia have been observed during administration of PACLITAXEL VIATRIS but generally do not require treatment. In severe cases, PACLITAXEL VIATRIS infusions may need to be interrupted or discontinued at the discretion of the treating medical practitioner. Frequent vital sign monitoring, particularly during the first hour of PACLITAXEL VIATRIS infusion, is recommended. Continuous cardiac monitoring is not required except for patients with serious conduction abnormalities. Cases of myocardial infarction have been reported. Congestive heart failure has been reported typically in patients who have received other chemotherapy, notably anthracyclines. Patients may experience severe cardiovascular events possibly related to PACLITAXEL VIATRIS administration and include: hypertension, venous thrombosis, ventricular tachycardia, and atrioventricular conduction block. ECG alterations are experienced by some patients. The most frequently reported are non-specific repolarisation abnormalities, sinus tachycardia and premature beats. The relationship between PACLITAXEL VIATRIS administration and ECG alterations is not clear.
Neurologic:
Neurologic symptoms may occur following the first course and the frequency of symptoms may increase with increasing exposure to PACLITAXEL VIATRIS. Sensory symptoms have usually improved or resolved within several months of PACLITAXEL VIATRIS discontinuation. Pre-existing neuropathies resulting from prior therapies are not a contraindication for PACLITAXEL VIATRIS therapy. Although the occurrence of peripheral neuropathy is frequent, the development of moderate to severe symptomatology is unusual and requires a dose reduction of 20 % for all subsequent courses of PACLITAXEL VIATRIS.
In non-small cell lung carcinoma patients, the administration of PACLITAXEL VIATRIS in combination with cisplatin resulted in greater incidence of neurotoxicity than usually seen in patients receiving single-agent PACLITAXEL VIATRIS.
Hepatic:
Patients with hepatic impairment may be at increased risk of toxicity particularly grade III-IV myelosuppression. Dose adjustment is recommended (see section 4.2). There is no evidence that the toxicity of PACLITAXEL VIATRIS is increased when given as a 3-hour infusion in patients with mildly abnormal liver function. No data are available for patients with severe baseline cholestasis. When PACLITAXEL VIATRIS is given as a 24-hour infusion to patients with moderate to severe hepatic impairment, increased myelosuppression may be seen as compared to patients with mildly elevated liver function tests given 24-hour infusions. Patients should be monitored closely for the development of profound myelosuppression. Hepatic necrosis and hepatic encephalopathy leading to death have been reported. Analysis restricted to patients with normal baseline liver function, shows instances of elevated bilirubin, elevated alkaline phosphate and elevated AST (SGOT).
Injection site reaction:
A specific treatment for extravasation reactions is unknown. Given the possibility of extravasation, it is advisable to closely monitor the infusion site for possible infiltration during administration.
Paediatric use:
The safety and effectiveness of PACLITAXEL VIATRIS in children have not been established (see section 4.3). There have been reports of central nervous system toxicity (including death) in a clinical trial in paediatric patients in which PACLITAXEL VIATRIS was infused intravenously over 3 hours at doses ranging from 350 mg/mu00b2 to 420 mg/mu00b2. The toxicity is most likely attributable to the high dose of the ethanol component of the PACLITAXEL VIATRIS vehicle given over a short infusion time. The use of concomitant antihistamines may intensify these effects. Although a direct effect of the paclitaxel itself cannot be discounted, the high doses used in this study (over twice the recommended adult dose) must be considered in assessing the safety of PACLITAXEL VIATRIS for use in this population.
Pseudomembranous colitis:
Pseudomembranous colitis has been reported, rarely, including cases in patients who have not received concurrent antibiotic treatment. This reaction should be considered in the differential diagnosis of severe or persistent cases of diarrhoea occurring during or shortly after treatment with PACLITAXEL VIATRIS.
A combination of pulmonary radiotherapy and PACLITAXEL VIATRIS treatment (irrespective of the order of the treatments) may promote the development of interstitial pneumonitis.
Fertility:
PACLITAXEL VIATRIS has been shown to be a teratogen, embryotoxic and a mutagen in several experimental systems. Therefore, female and male patients of reproductive age must take contraceptive measures for themselves and/or their sexual partners during and for at least 6 months after therapy (see section 4.6). Male patients are advised to seek advice on conservation of sperm prior to treatment because of the possibility of irreversible infertility due to therapy with PACLITAXEL VIATRIS.
Macular oedema:
There have been reports of reduced visual acuity due to cystoid macular oedema (CME) during treatment with PACLITAXEL VIATRIS. Patients with visual impairment during PACLITAXEL VIATRIS treatment should seek a prompt and complete ophthalmologic examination. Discontinue PACLITAXEL VIATRIS treatment if a CME diagnosis is confirmed.
Excipients:
PACLITAXEL VIATRIS contains dehydrated alcohol, 39,5 % v/v. Consideration should be given to possible central nervous system and other effects of alcohol for all patients. Children may be more sensitive than adults to the effects of alcohol. PACLITAXEL VIATRIS contains polyoxyethylated castor oil which may cause severe allergic reactions.
4.5 Interaction with other medicines and other forms of interaction
Cisplatin: The recommended regimen of PACLITAXEL VIATRIS administration for the primary treatment of ovarian carcinoma is for PACLITAXEL VIATRIS to be given before cisplatin. When PACLITAXEL VIATRIS is given before cisplatin, the safety profile of PACLITAXEL VIATRIS is consistent with that reported for single-agent use. When PACLITAXEL VIATRIS was given after cisplatin, patients showed a more profound myelosuppression and an approximately 33 % decrease in paclitaxel clearance. Patients treated with PACLITAXEL VIATRIS and cisplatin may have an increased risk of renal failure as compared to cisplatin alone in gynaecological cancers.
Ketoconazole: Medicines concomitantly administered with PACLITAXEL VIATRIS (e.g. corticosteroids, antihistamines, and H 2 antagonists) did not appear to interact adversely, however, possible interactions of PACLITAXEL VIATRIS with concomitantly administered medicines have not been formally investigated. Based on in vitro data, there is the possibility of an inhibition of PACLITAXEL VIATRIS metabolism in patients treated with ketoconazole. As a result, caution should be exercised when treating patients with PACLITAXEL VIATRIS when they are receiving ketoconazole as concomitant therapy.
Doxorubicin: Plasma levels of doxorubicin and doxorubicinol may be increased when PACLITAXEL VIATRIS and doxorubicin are used in combination. Sequence effects characterised by more profound neutropenic and stomatitis episodes, have been observed with combination use of PACLITAXEL VIATRIS and doxorubicin, when PACLITAXEL VIATRIS was administered before doxorubicin and using longer than recommended infusion times.
Active substances metabolised in the liver: The metabolism of paclitaxel is catalysed by cytochrome P450 isoenzymes CYP2C8 and CYP3A4. Caution should be exercised when administering PACLITAXEL VIATRIS concomitantly with known substrates or inducers or inhibitors of these isoenzymes, (e.g. ketoconazole and other imidazole antifungals, erythromycin, fluoxetine, gemfibrozil, clopidogrel, cimetidine, ritonavir, saquinavir, indinavir, and nelfinavir) because toxicity of PACLITAXEL VIATRIS may be increased due to higher paclitaxel exposure. Administering PACLITAXEL VIATRIS concomitantly with medicines known to induce either CYP2C8 or CYP3A4 (e.g. rifampicin, carbamazepine, phenytoin, efavirenz, nevirapine) is not recommended because efficacy may be compromised because of lower paclitaxel exposures.
PVC equipment: Contact of the undiluted concentrate with plasticised polyvinyl chloride (PVC) equipment or devices used to prepare solutions for infusion is not recommended. In order to minimise patient exposure to the plasticiser DEHP [di-(2-ethylhexyl)phthalate], which may be leached from PVC infusion bags or sets, diluted PACLITAXEL VIATRIS solutions should preferably be stored in bottles (glass, polypropylene) or plastic bags (polypropylene, polyolefin) and administered through polyethylene-lined administration sets. PACLITAXEL VIATRIS should be administered through an in-line filter with a microporous membrane not greater than 0,22 microns. Use of filter devices such as IVEX-2 filters which incorporate short inlet and outlet PVC-coated tubing has not resulted in significant leaching of DEHP.
4.6 Fertility, pregnancy and lactation
Women of childbearing potential / Contraception in males and females: Women of childbearing potential should be advised to avoid becoming pregnant during therapy with PACLITAXEL VIATRIS and to inform the treating medical practitioner immediately should this occur. Female and male patients of fertile age, and/or their partners should use contraception for at least 6 months after treatment with PACLITAXEL VIATRIS.
Pregnancy: PACLITAXEL VIATRIS should not be used during pregnancy. There is no information on the use of PACLITAXEL VIATRIS in pregnant women. PACLITAXEL VIATRIS may cause foetal harm when administered to pregnant women.
Breastfeeding: It is not known whether PACLITAXEL VIATRIS is excreted in human milk. Breastfeeding should be discontinued for the duration of PACLITAXEL VIATRIS therapy.
Fertility: PACLITAXEL VIATRIS has been shown to be embryotoxic, foetotoxic and to decrease fertility in animal studies. Male patients should seek advice regarding cryo-conservation of sperm prior to treatment with PACLITAXEL VIATRIS because of the possibility of infertility.
4.7 Effects on ability to drive and use machines
PACLITAXEL VIATRIS contains alcohol which may impair the ability to drive or operate machines. Consideration should be given to possible CNS and other effects of alcohol.
4.8 Undesirable effects
a. Summary of the safety profile
The frequency and severity of adverse events are generally similar between patients receiving PACLITAXEL VIATRIS for the treatment of ovarian, breast or lung carcinoma. None of the observed toxicities were clearly influenced by age.
b. Tabulated list of adverse reactions
| System organ class | Frequency | Adverse reaction |
|---|---|---|
| Infections and infestations | Frequent | Infection (mainly urinary tract infections and infections in the upper respiratory tract), with reported cases of fatal outcome |
| Less frequent | Septic shock, pneumonia, peritonitis, sepsis | |
| Blood and lymphatic system disorders | Frequent | Myelosuppression, neutropenia, anaemia, thrombocytopenia, leucopenia, bleeding |
| Less frequent | Febrile neutropenia, acute myeloid leukaemia, myelodysplastic syndrome | |
| Frequency unknown | Disseminated intravascular coagulation (DIC) | |
| Immune system disorders | Frequent | Mild hypersensitivity reactions (mainly flushing and rash) |
| Less frequent | Significant hypersensitivity reactions requiring treatment (e.g. hypotension, angioneurotic oedema, respiratory distress, generalised urticaria, chills, back pain, chest pain, tachycardia, abdominal pain, pain in extremities, diaphoresis and hypertension), anaphylactic reactions, anaphylactic shock | |
| Frequency unknown | Bronchospasm | |
| Metabolism and nutrition disorders | Less frequent | Anorexia, dehydration |
| Frequency unknown | Tumour lysis syndrome | |
| Psychiatric disorders | Less frequent | Confusional state |
| Nervous system disorders | Frequent | Neurotoxicity (mainly peripheral neuropathy; can persist beyond 6 months of PACLITAXEL VIATRIS discontinuation) |
| Less frequent | Motor neuropathy (with resultant minor distal weakness), autonomic neuropathy (resulting in paralytic ileus and orthostatic hypotension), grand mal seizures, convulsions, encephalopathy, dizziness, headache, ataxia | |
| Eye disorders | Less frequent | Optic nerve and/or visual disturbances (scintillating scotomata), particularly in patients who have received higher doses than recommended |
| Frequency unknown | Macular oedema, photopsia, vitreous floaters | |
| Ear and labyrinth disorders | Less frequent | Ototoxicity, loss of hearing, tinnitus, vertigo |
| Cardiac disorders | Frequent | Abnormal ECG, bradycardia |
| Less frequent | Cardiomyopathy, asymptomatic ventricular tachycardia, tachycardia with bigeminy, AV-block and syncope, myocardial infarction, cardiac failure, atrial fibrillation, supraventricular tachycardia | |
| Vascular disorders | Frequent | Hypotension |
| Less frequent | Hypertension, thrombosis, thrombophlebitis, shock | |
| Frequency unknown | Phlebitis | |
| Respiratory, thoracic and mediastinal disorders | Less frequent | Dyspnoea, pleural effusion, interstitial pneumonia, lung fibrosis, pulmonary embolism, respiratory failure, cough |
| Gastrointestinal disorders | Frequent | Nausea, vomiting, diarrhoea, mucositis |
| Less frequent | Bowel obstruction, bowel perforation, ischaemic colitis, pancreatitis, mesenteric thrombosis, pseudomembranous colitis, oesophagitis, constipation, ascites, neutropenic colitis | |
| Hepatobiliary disorders | Less frequent | Hepatic necrosis (with fatal outcome), hepatic encephalopathy (with fatal outcome) |
| Skin and subcutaneous tissue disorders | Frequent | Alopecia, transient and mild nail and skin changes |
| Less frequent | Pruritus, rash, erythema, Stevens-Johnson syndrome, epidermal necrolysis, erythema multiforme, exfoliative dermatitis, urticaria, onycholysis (patients on therapy should wear sun protection on hands and feet) | |
| Frequency unknown | Palmar-plantar erythrodysesthesia syndrome | |
| Musculoskeletal, connective tissue and bone disorders | Frequent | Arthralgia, myalgia |
| Frequency unknown | Systemic lupus erythematosus, scleroderma | |
| General disorders and administration site conditions | Frequent | Injection site reactions (including localised oedema, pain, erythema, induration, extravasation with phlebitis or cellulitis, skin fibrosis and skin necrosis) |
| Less Frequent | Asthenia, pyrexia, oedema, malaise | |
| Investigations | Frequent | Severe elevation of AST (SGOT), severe elevation of alkaline phosphatise |
| Less frequent | Severe elevation in bilirubin, increase in blood creatinine |
c. Description of selected adverse reactions
Unless otherwise noted, the following discussion refers to published information on the overall safety database of 812 patients with solid tumours treated with single-agent paclitaxel in clinical studies administered as one of two doses (135 or 175 mg/mu00b2) and one of the two schedules (3 or 24 hours) in the metastatic setting.
Haematological toxicities: Bone marrow suppression was the major dose-limiting toxicity of PACLITAXEL VIATRIS. Neutropenia, the most important haematological toxicity, was dose and schedule dependent and was generally rapidly reversible. Severe neutropenia (< 500 cells/mmu00b3) was more frequent with the 24-hour than with the 3-hour infusion; infusion duration had a greater impact on myelosuppression than dose. Neutropenia did not appear to increase with cumulative exposure and did not appear to be more frequent nor more severe for patients previously treated with radiation therapy. Infectious episodes occurred very commonly and were fatal in 1 % of all patients, and included sepsis, pneumonia and peritonitis. Urinary tract infections and upper respiratory tract infections were the most frequently reported infectious complications. The use of supportive therapy, including G-CSF, is recommended for patients who have experienced severe neutropenia. Twenty percent of the patients experienced a drop in their platelet count below 100 000 cells/mmu00b3 at least once while on treatment; 7 % had a platelet count < 50 000 cells/mmu00b3 at the time of their worst nadir. Bleeding episodes were reported in 4 % of all courses and by 14 % of all patients but most of the haemorrhagic episodes were localised and the frequency of these events was unrelated to the PACLITAXEL VIATRIS dose and schedule.
Neurologic: In general, the frequency and severity of neurologic manifestations were dose dependent in patients receiving single-agent PACLITAXEL VIATRIS. The frequency of peripheral neuropathy increased with cumulative dose. Paraesthesia commonly occurs in the form of hyperaesthesia. Peripheral neuropathy was the cause of PACLITAXEL VIATRIS discontinuation in 1 % of all patients. Sensory symptoms have usually improved or resolved within several months of PACLITAXEL VIATRIS discontinuation. Pre-existing neuropathies resulting from prior therapies are not a contraindication for PACLITAXEL VIATRIS therapy. Infrequent reports in the literature of abnormal visual evoked potentials in patients have suggested persistent optic nerve damage.
Hypersensitivity reactions (HSR): All patients in clinical trials received premedication prior to PACLITAXEL VIATRIS therapy. The frequency and severity of HSR were not affected by the dose or schedule of PACLITAXEL VIATRIS administration. The most frequent symptoms observed during these severe reactions were dyspnoea, flushing, chest pain and tachycardia. A significant hypersensitivity reaction with possible fatal outcome (defined as hypotension requiring therapy, angioedema, respiratory distress requiring bronchodilator therapy, or generalised urticaria) occurred in two (< 1 %) patients. Thirty-four percent of patients (17 % of all courses) experienced minor hypersensitivity reactions. Abdominal pain, pain in the extremities, diaphoresis and hypertension are also noted. Minor hypersensitivity reactions, mainly flushing and rash, did not require therapeutic intervention nor did they prevent continuation of PACLITAXEL VIATRIS therapy.
Injection site reactions: During intravenous administration, injection site reactions were usually mild and consisted of localised oedema, pain, erythema, tenderness and indurations; on occasion, extravasations can result in cellulitis. Skin sloughing and/or peeling has been reported sometimes related to extravasations. Skin discolouration may also occur. These reactions have been observed more frequently with the 24-hour infusion than with the 3-hour infusion. In some cases, the onset of the injection site reaction either occurred during a prolonged infusion or was delayed by a week to 10 days.
Cardiovascular: Hypotension, during the first 3 hours of infusion, occurred in 12 % of all patients and 3 % of all courses administered. Bradycardia, during the first 3 hours of infusion, occurred in 3 % of all patients and 1 % of all courses. ECG alterations in the form of re-polarisation abnormalities like sinus tachycardia, sinus bradycardia, and premature beats have been observed in clinical studies. Severe cardiac conduction abnormalities have been reported in < 1 % of patients during PACLITAXEL VIATRIS therapy. If patients develop significant conduction abnormalities during PACLITAXEL VIATRIS administration, appropriate therapy should be administered and continuous electrocardiographic monitoring should be performed during subsequent therapy with PACLITAXEL VIATRIS.
Gastrointestinal (GI) toxicity: Mild to moderate nausea, vomiting, diarrhoea and mucositis (also reported as pharyngitis or cheilitis) were reported frequently by all patients. Mucositis was schedule dependent and occurred more frequently with the 24-hour than with the 3-hour infusion. Less frequent reports of neutropenic enterocolitis (typhilitis), despite the co-administration of G-CSF, were observed in patients treated with PACLITAXEL VIATRIS alone and in combination with other chemotherapeutic medicines. PACLITAXEL VIATRIS and cisplatin: Cross-study comparison of neurotoxicity suggests that when PACLITAXEL VIATRIS is given in combination with cisplatin 75 mg/mu00b2, the incidence of severe neurotoxicity is more common at a PACLITAXEL VIATRIS dose of 175 mg/mu00b2 given by 3-hour infusion (21 %) than at a dose of 135 mg/mu00b2 given by 24-hour infusion (3 %). PACLITAXEL VIATRIS and radiotherapy: radiation pneumonitis has been reported in patients receiving concurrent radiotherapy.
Reporting of suspected adverse reactions: Reporting suspected adverse reactions after authorisation of the medicine is important. It allows continued monitoring of the benefit/risk balance of the medicine. Health care providers are asked to report any suspected adverse reactions to SAHPRA via the u201c6.04 Adverse Drug Reactions Reporting Formu201d, found online under SAHPRAu2019s publications: https://www.sahpra.org.za/Publications/Index/8
4.9 Overdose
There is no antidote for PACLITAXEL VIATRIS overdosage. The primary anticipated complications of overdosage would consist of bone marrow suppression, peripheral neurotoxicity and mucositis. Overdoses in paediatric patients may be associated with acute ethanol toxicity. In case of overdose, the patient should be closely monitored. Treatment is symptomatic and supportive.
